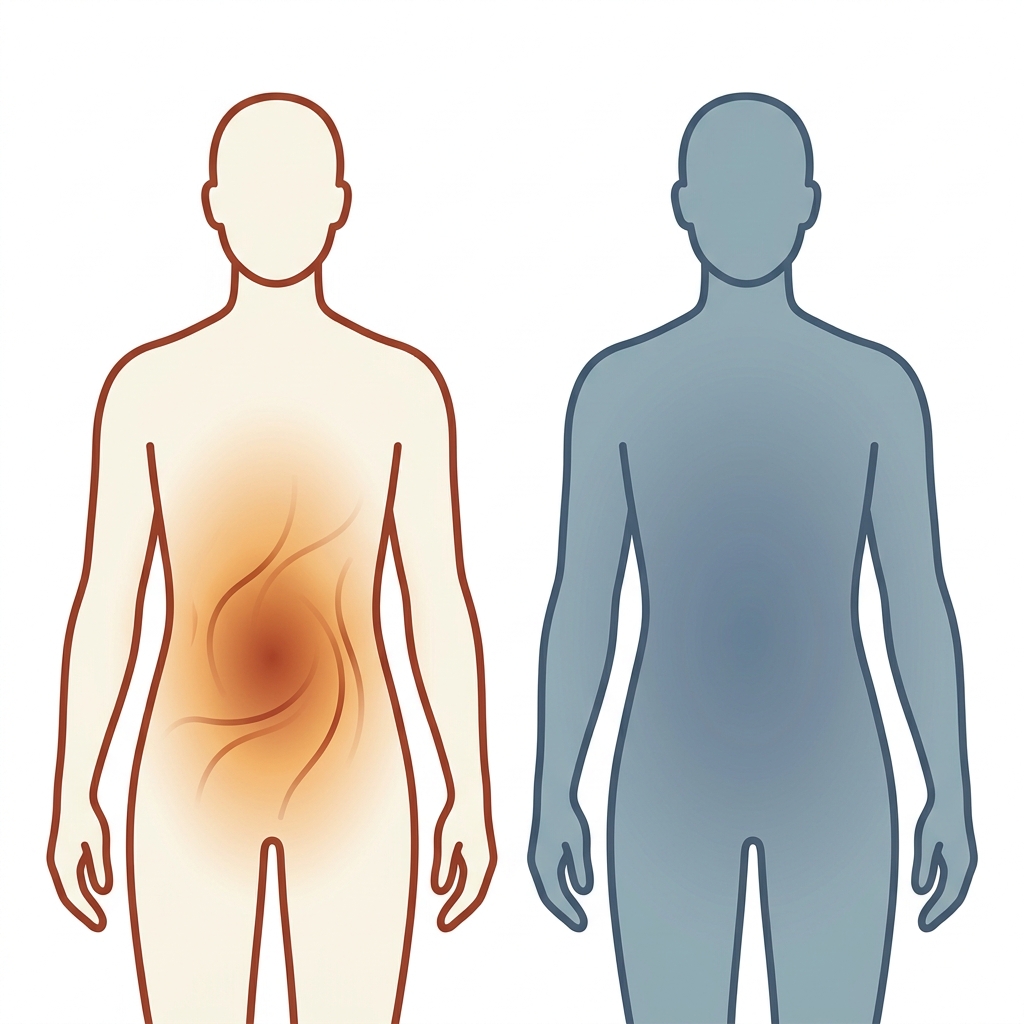
Two people can walk into a clinic sharing an identical BMI, look nearly the same in the mirror, and step off a standard scale with matching numbers. Yet one may carry a metabolic risk profile that is genuinely concerning while the other is metabolically healthy. That difference is invisible to a scale. It is only revealed by body composition scanning.
This is the central point worth understanding: body composition scanning is a clinical tool, not a one-time data event. The numbers it produces are only meaningful when interpreted against a person’s full metabolic picture. A printout of percentages, read in isolation, tells a limited story.
Three threads run through this discussion. First, the “skinny fat” phenomenon, clinically known as Metabolically Obese Normal Weight (MONW), where a normal BMI conceals dangerous composition. Second, the value of serial scanning over time rather than a single snapshot. Third, the growing use of scanning to monitor muscle preservation during metabolic treatment.
This article goes beyond listing methods and accuracy figures. It explains what results actually mean and how a clinician uses them. That matters most for adults navigating age-related metabolic change, those curious about metabolic treatment, and anyone who has been told their weight is “normal” but still senses something is off.
What Body Composition Scanning Actually Measures
Scanning quantifies four core compartments that BMI and standard scales cannot: fat mass, lean (muscle) mass, bone mineral density, and visceral fat.
Each matters independently. Fat location (visceral versus subcutaneous) largely determines metabolic risk. Lean mass predicts longevity and functional capacity. Bone density informs fracture risk. This is where the “BMI paradox” appears: BMI cannot distinguish skeletal muscle from visceral adipose tissue or ectopic fat, potentially obscuring high-risk phenotypes such as sarcopenia, myosteatosis, and sarcopenic obesity.
As the body ages, fat mass tends to rise while lean mass declines, a shift invisible on a scale but clearly captured by scanning. One clinical distinction worth flagging: “fat-free mass” is not the same as “skeletal muscle mass,” and that difference matters especially when monitoring patients on metabolic treatment.
Scanning is now used across endocrinology, geriatrics, sports medicine, oncology, and longevity medicine, not just fitness contexts.
The Methods: A Clinical Comparison
The goal here is not a gym-marketing checklist. It is helping readers understand which method suits their situation and why accuracy differences carry clinical weight.
DEXA (Dual-Energy X-ray Absorptiometry): The Clinical Gold Standard
DEXA uses two low-energy X-ray beams to differentiate fat mass, lean mass, and bone mineral density simultaneously. Its margin of error for body fat percentage is roughly ±1 to 2%, with radiation exposure equivalent to about 30 millirem, which is minimal and clinically acceptable.
In a single 10- to 20-minute scan, DEXA uniquely provides regional fat distribution (android versus gynoid), visceral fat estimation, appendicular lean mass index, and bone mineral density. Its key limitation: results can vary by machine manufacturer and software version, which is why using the same machine for serial scans is essential for reliable longitudinal tracking. For clinical decisions involving visceral fat, muscle mass, or bone density, DEXA is the preferred standard.
BIA Devices (e.g., InBody): Accessible but Sensitive to Conditions
BIA sends a low electrical current through the body and estimates composition based on resistance, since different tissues conduct electricity differently. Its margin of error runs ±5 to 8% versus DEXA, a clinically significant range that can misclassify a person’s risk category.
BIA readings are sensitive to hydration status, recent food intake, exercise timing, and ambient room temperature, all variables unrelated to actual composition. BIA devices consistently underestimate fat mass and overestimate fat-free mass compared to DEXA. Used under standardized conditions, they are more informative than a standard scale and can serve as a monitoring aid, but not a substitute for DEXA in clinical decision-making. University of Rochester Medical Center guidance notes that InBody scans track trends better than scales, while long-term health assessment should also incorporate proven markers like blood pressure, cholesterol, and blood sugar.
The Bod Pod (Air Displacement Plethysmography): Useful but Limited
The Bod Pod measures body volume by detecting air displaced when a person sits inside a sealed chamber, then calculates density to estimate fat versus fat-free mass. Its margin of error is roughly 2 to 3%, better than BIA but still short of DEXA.
Its primary limitation is scope: it measures total fat versus fat-free mass only, with no regional breakdown, no visceral fat data, no appendicular lean mass, and no bone density. Results are also affected by clothing, body hair, and breathing patterns. Like BIA, it underestimates fat mass and overestimates fat-free mass versus DEXA. It suits research settings and populations where DEXA is unavailable.
MRI, CT, and AI-Powered Imaging: The Emerging Frontier
MRI and CT are the most precise methods for quantifying specific tissue types, particularly visceral adipose tissue and intramuscular fat, but are expensive, time-intensive, and not routine for monitoring. A landmark 2026 RSNA/Radiology study applied AI to whole-body MRI scans from 66,608 participants, associating high visceral fat with 2.26 times increased diabetes risk, high intramuscular fat with 1.54 times increased cardiovascular event risk, and low skeletal muscle with 1.44 times higher all-cause mortality. As the largest AI-powered body composition study to date, it establishes population-level reference curves.
Emerging smartphone AI tools trained on large datasets (roughly 35,323 UK Biobank participants) have achieved mean absolute error near 2.15% for total body fat percentage versus DEXA in research settings. For now, these are best used as triage and monitoring aids rather than standalone diagnostics, since accuracy varies by skin tone, clothing, and image quality. A 2026 Frontiers in Medical Technology review confirms the field is developing rapidly.
Why Accuracy Differences Matter Clinically, Not Just Statistically
A ±5 to 8% BIA error is not an abstract statistic. It can be the difference between “metabolically healthy” and “at risk.” A person measured at 25% body fat on DEXA could read anywhere from 17% to 33% on BIA under suboptimal conditions, a range spanning “athletic” to “clinically elevated.”
For serial tracking, standardization is everything. If a BIA reading shifts 4% between visits because of hydration rather than real change, the clinical team is chasing noise, not signal. DEXA is far less sensitive to those variables. Even so, AJCN 2026 methodological standards note that DXA accuracy varies with reference method, population, and equipment model, reinforcing the same-machine rule. The method should match the clinical question. For metabolic risk assessment and longitudinal monitoring, DEXA is the appropriate standard.
The “Skinny Fat” Problem: When Normal BMI Conceals Dangerous Composition
The MONW phenotype describes individuals with normal BMI who carry dangerous visceral fat, invisible to a scale but clear on a scan. A 2026 Mayo Clinic Proceedings review confirms these individuals face increased risk for type 2 diabetes, cardiovascular disease, and cancer. A 2023 cross-sectional study of 3,001 adults found that 26% of normal-BMI men and 38% of normal-BMI women had excess body fat by DEXA, yet BMI alone would have labeled them “healthy.”
The mechanism is biological: visceral fat secretes inflammatory cytokines including interleukin-6 and TNF-alpha that disrupt insulin signaling and raise blood pressure. Subcutaneous fat under the skin is metabolically less active; visceral fat surrounding the organs is the dangerous compartment BMI cannot detect. Someone told “your weight is fine” may still benefit meaningfully from scanning if they carry risk factors, family history, or symptoms. This is precisely why sound metabolic health assessment goes beyond the scale.
Sarcopenia and the Aging Body: The Muscle Loss Risk Most Exams Miss
Sarcopenia, clinically defined as low muscle mass and strength, is rarely assessed directly in routine exams, yet it carries real mortality risk. Adults with sarcopenia face a 1.5 to 2 times higher risk of death over five years. Muscle mass declines 3 to 8% per decade after age 35, accelerating to roughly 25% per decade after 70. The ARIC cohort study (2026) shows sarcopenia prevalence rising from about 5% at ages 65 to 69 to 36% at ages 85 to 89.
This deterioration hides on a scale. As muscle is lost and fat gained, total weight can remain stable, masking the underlying shift. The sarcopenic obesity phenotype (losing muscle while gaining fat) is a high-risk combination BMI cannot identify. Catching muscle loss early allows targeted intervention: resistance training, protein optimization, and where appropriate, hormonal support. Adults 40 and older who feel their body has changed despite steady weight and habits are often experiencing exactly this shift.
Body Composition Scanning During Metabolic Treatment: The Muscle Preservation Imperative
This is the fastest-growing clinical use case and the one most underserved by existing content. When a patient loses weight on a GLP-1 medication, the key question is how much of that loss is fat versus lean muscle.
It matters because losing lean mass is not neutral. It lowers metabolic rate, impairs function, accelerates age-related muscle decline, and can worsen long-term metabolic health even as the scale improves. Clinical evidence indicates GLP-1 medications reduce fat mass more than lean body mass, but periodic body composition monitoring is recommended, especially in higher-risk patients, to confirm muscle preservation. A 2026 PubMed review on lean mass preservation during GLP-1 treatment describes nutrition, supplementation, exercise, and monitoring as components of protecting lean mass, function, bone health, and nutritional adequacy.
Regulation is shifting as well: the January 2025 FDA draft guidance on obesity drug development now identifies body composition parameters as crucial secondary endpoints, signaling a move away from weight-only metrics. A baseline scan before treatment, followed by regular scans, reveals whether a patient is preserving lean mass, losing primarily fat, and maintaining bone density. This is precisely where Red Mountain’s programs, designed to support patients on weight-loss medications by minimizing side effects, preserving muscle mass, and maintaining nutrient balance, add clinical value.
Serial Scanning: Why One Snapshot Is Never Enough
A single scan is a data point; serial scans are a clinical story, and the story drives intervention. A baseline establishes reference values for fat mass, lean mass, visceral fat, appendicular lean mass index, and bone density. A reasonable cadence is every 6 to 12 weeks during active treatment and annually for maintenance.
Trends reveal what snapshots hide. A patient whose visceral fat falls while lean mass holds is responding well; one whose lean mass drops alongside fat needs an adjustment. For reliability, the same machine (ideally the same DEXA unit) should be used at each visit. For adults 40 and older focused on sustained metabolic health, regular scanning is as important as annual labs or blood pressure checks.
Interpreting the Numbers: What the Key Metrics Actually Mean
This is the interpretation layer most content omits, and the reason a scan without clinical context has limited value.
Body Fat Percentage and Age/Sex Centile
Absolute body fat percentage matters less than percentage relative to age- and sex-matched peers. A 30% reading means something different for a 35-year-old woman than a 65-year-old man. The 2026 RSNA/Radiology study offers open-source z-score calculators derived from 66,608 participants. Elevated body fat raises risk of cardiovascular disease, type 2 diabetes, several cancers, and early mortality, but the threshold is age- and sex-specific. No single number should dominate the interpretation; visceral fat, lean mass, and distribution matter as much or more.
Visceral Fat Level
Visceral fat is stored around the abdominal organs and is the primary driver of metabolic disease risk. The 2026 RSNA/Radiology finding associates high visceral fat with 2.26 times increased diabetes risk, among the strongest body composition predictors identified. DEXA estimates it via the android region scan, which is less precise than MRI or CT but useful for monitoring trends. A normal total fat percentage with elevated visceral fat signals higher risk than the overall number suggests: MONW in practice.
Appendicular Lean Mass Index (ALMI)
Appendicular lean mass is the combined muscle of the arms and legs, the most clinically relevant skeletal muscle measure for function and longevity. ALMI divides that mass by height squared for comparison across body sizes. Low ALMI is a diagnostic criterion for sarcopenia, and the 2026 study associated low skeletal muscle with 1.44 times higher all-cause mortality. During treatment, a declining ALMI is a clinical signal requiring intervention and validates whether resistance training and protein strategies are working.
Android-to-Gynoid Fat Ratio
Android fat sits in the trunk (higher risk); gynoid fat sits in the hips and thighs (lower risk). A high ratio indicates central adiposity, the pattern most tied to insulin resistance and metabolic syndrome. This ratio comes from DEXA regional analysis, not BIA or Bod Pod. Effective treatment tends to reduce android fat preferentially, improving the ratio over time.
Bone Mineral Density
DEXA measures bone mineral density simultaneously, a benefit other methods lack. BMD declines with age and accelerates with low body weight, hormonal changes (particularly estrogen decline in perimenopause and menopause), and inadequate calcium and vitamin D. Significant weight loss, including during treatment, can speed bone loss if not managed with nutrition and resistance training. For adults 40 and older, tracking BMD alongside muscle and visceral fat completes the clinical picture.
The 2025 to 2026 Regulatory and Clinical Consensus Shift
The January 2025 FDA draft guidance now emphasizes long-term fat mass reduction rather than weight reduction alone, encouraging imaging-based assessments to distinguish fat from lean mass loss. The 2025 AACE consensus update recommends assessing fat mass using BMI plus waist-to-height ratio, reserving DXA or impedance plethysmography for cases where measurements and clinical findings disagree. The 2026 AJCN methodological standards, authored by an international working group of 29 experts, standardized terminology and guidance across the field. Together, these developments confirm that body composition is moving from a fitness tool to a clinical standard.
What to Do After a Scan: Turning Numbers Into a Clinical Plan
A scan result without interpretation has limited value. The numbers become actionable only within a person’s full context: history, symptoms, and goals. A provider should ask: Is visceral fat elevated for this age and sex? Is lean mass declining? Is the android-to-gynoid ratio improving or worsening? Is bone density appropriate for this age?
Data guides specifics. Elevated visceral fat may prompt dietary changes, metabolic assessment, and closer monitoring. Low ALMI may prompt a resistance protocol and protein adjustment. Declining BMD may prompt hormonal evaluation and supplement review. For patients on GLP-1 medications, scan data informs whether the protocol needs adjusting to better protect lean mass. Scanning complements, but never replaces, standard labs. This interpretation layer is where a practice with 30-plus years of metabolic patient outcomes adds value: not handing over a printout, but explaining what it means and building a plan around it.
Conclusion: The Scan Is the Beginning, Not the Answer
Body composition scanning is a powerful clinical tool, but only as part of an ongoing, interpreted process rather than a one-time event. Three insights carry the point: normal BMI does not equal metabolic health; serial scanning reveals trends a single snapshot never can; and monitoring lean mass preservation during metabolic treatment is now among the most important applications of scanning. The 2025 FDA draft guidance, the 2026 RSNA/Radiology AI-MRI study, and the AJCN standards all point in the same direction.
For anyone who has been told their weight is normal but something still feels off, or who is on a metabolic treatment program and wants to know whether muscle is being preserved, a clinically interpreted scan is the appropriate next step. The goal is not a number on a printout. It is a clear understanding of where the body is today, where it is trending, and what to do about it.
Ready to Understand Your Body Composition?
For those who recognize the patterns described here, a clinical body composition assessment is usually the clearest next step: not to add another number to a file, but to understand what that number means for metabolic health.
Red Mountain brings 30-plus years of metabolic patient outcomes, in-person providers, and programs designed to support people through every stage of their metabolic health journey, from initial assessment through long-term maintenance. Body composition monitoring is part of that broader approach to metabolic correction, including support for patients on weight-loss medications who want to ensure they are preserving lean mass alongside fat loss.
This is the kind of conversation that happens in every consult: not just what the scan shows, but what it means and what to do next.